Specialised surgical evaluation and treatment planning for selected neuroendocrine tumours, including gastrointestinal and pancreatic NETs.
Neuroendocrine tumours can behave differently depending on their location, grade, stage and biological characteristics. Treatment planning therefore requires careful review of pathology, imaging and the overall clinical situation.
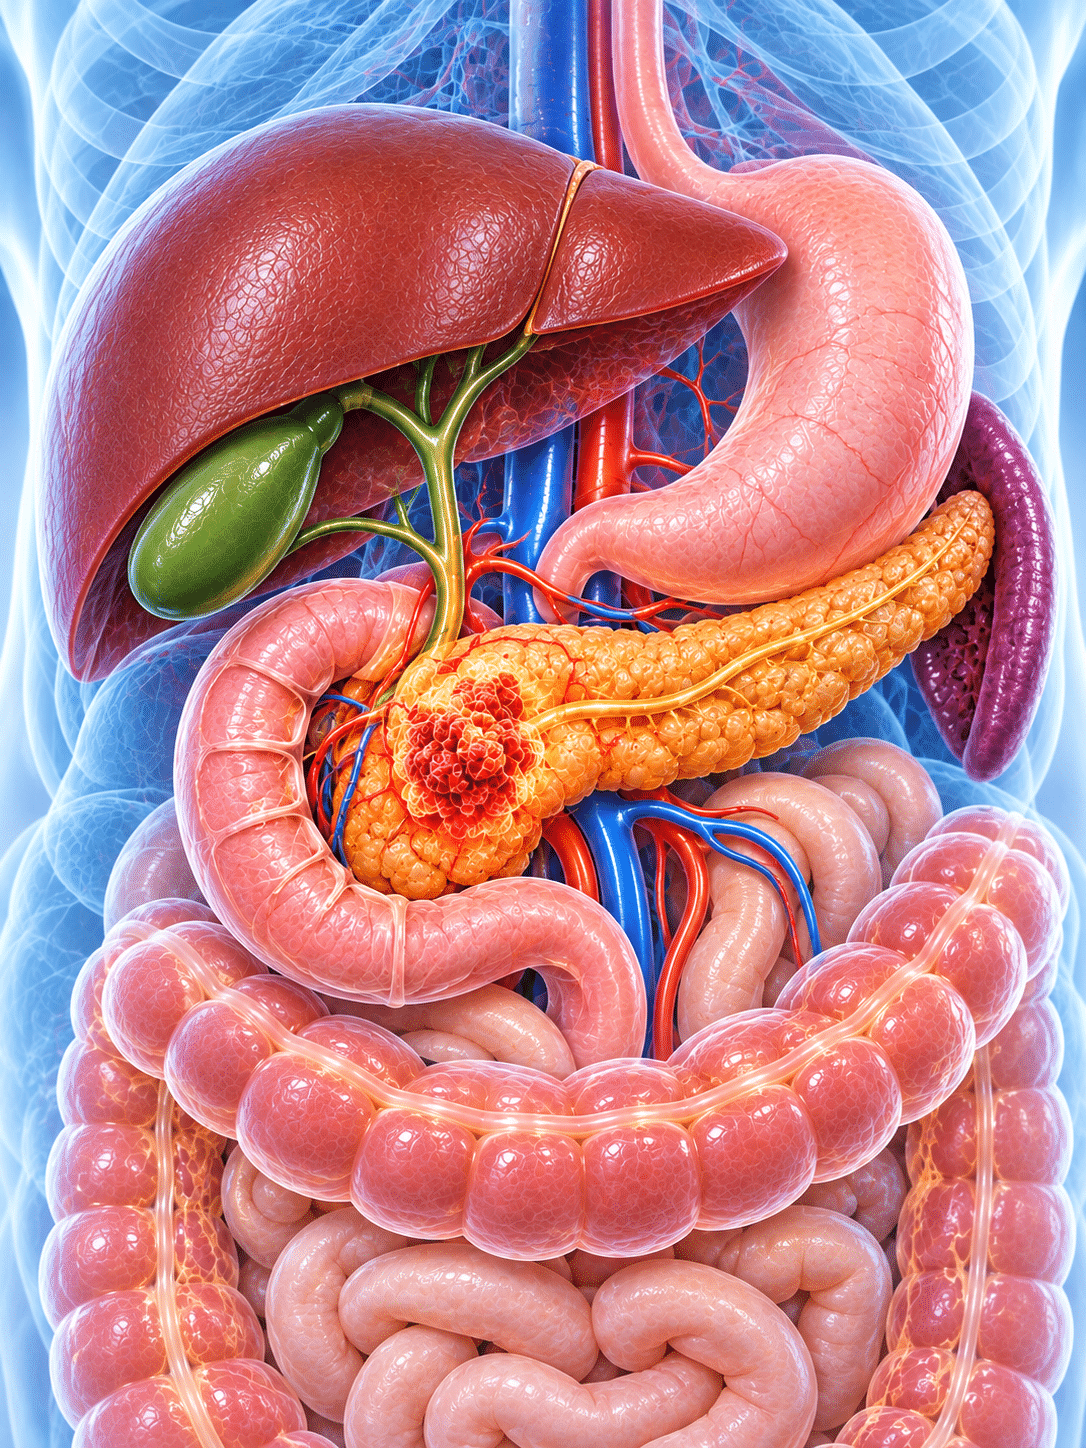
Neuroendocrine tumours, or NETs, are tumours that arise from neuroendocrine cells. They can develop in different organs and may have different patterns of growth and behaviour.
Gastrointestinal and pancreatic neuroendocrine tumours may require a combination of diagnostic, surgical and medical treatment approaches depending on the tumour's location, grade, stage and other clinical findings.
Surgery may have a role in selected patients. The appropriate approach is determined after reviewing pathology, imaging, disease extent and the patient's overall health.
The treatment plan depends on tumour location, grade, stage, resectability, imaging findings, pathology and the patient's overall clinical condition.
The location of a neuroendocrine tumour influences symptoms, investigations and treatment planning.
Neuroendocrine tumours can develop in the small intestine and may require evaluation of the primary tumour and any associated disease spread.
Gastric NETs may have different clinical characteristics, making appropriate endoscopic, pathological and clinical assessment important.
Pancreatic neuroendocrine tumours may require detailed assessment of the tumour's location, size, biological characteristics and relationship with surrounding structures.
Neuroendocrine tumours may also arise in the appendix or colon, where treatment depends on tumour characteristics and disease extent.
Neuroendocrine tumours are not all the same. Their grade, differentiation, proliferation characteristics and stage can influence the treatment approach.
The grade reflects how quickly the tumour cells are dividing and is an important part of determining the biological behaviour of a NET.
Pathology helps determine whether a tumour is well differentiated or has features requiring a different treatment strategy.
Assessment of the primary tumour, lymph nodes and possible distant disease helps establish the overall extent of the cancer.
Some neuroendocrine tumours can produce hormones and may cause symptoms related to hormone release, while others may not.
The organ and exact anatomical location of the tumour influence the possible surgical approach and treatment strategy.
Age, general health, previous treatments and other medical factors are considered when developing an individual treatment plan.
Some neuroendocrine tumours may cause no symptoms for a long time, while others may produce symptoms because of their location or hormone activity.
Abdominal pain, discomfort, bloating or changes in bowel habits may occur depending on the tumour location.
Diarrhoea or other bowel changes can occur in some patients, particularly with certain hormone-producing NETs.
Episodes of flushing may occur with some hormone-producing neuroendocrine tumours.
Weight changes, fatigue or other unexplained symptoms may occur but are not specific to NETs and require proper medical evaluation.
Diagnosis of a neuroendocrine tumour may involve several investigations. The exact combination depends on the suspected tumour location and clinical presentation.
Pathology is particularly important because neuroendocrine tumours are evaluated using specific pathological and biological characteristics.
Treatment planning begins with understanding the tumour's location, grade, stage and extent of disease.
Tissue examination helps establish the diagnosis and provides important information about tumour differentiation and grade.
Additional pathological markers may be used to support the diagnosis and classification of a neuroendocrine tumour.
Cross-sectional imaging may help assess the primary tumour, surrounding anatomy and possible disease spread.
In appropriate cases, specialised functional imaging may help identify neuroendocrine tumour sites and assess disease extent.
Depending on the suspected location, upper GI endoscopy or other endoscopic evaluation may be used to identify and assess a tumour.
Additional blood or biochemical tests may be considered depending on the suspected type and hormone activity of the NET.
Surgery may be considered for selected neuroendocrine tumours depending on tumour location, resectability, disease extent and the patient's overall condition.
When a NET is localized and surgically removable, resection of the primary tumour may be considered as part of the treatment plan.
Minimally invasive surgery may be considered for selected NET procedures when the tumour location, anatomy and planned operation are suitable.
More complex cases may require detailed assessment of anatomy, disease extent and the relationship of the tumour with nearby organs and blood vessels.
Pancreatic NET surgery requires careful assessment of tumour location, size, relationship with the pancreatic duct and surrounding structures.
Small bowel NETs may require assessment of the primary tumour, nearby lymph nodes and the extent of mesenteric disease.
Depending on the tumour and stage, regional lymph nodes may need to be assessed or removed during surgical treatment.
When disease has spread, surgery may still have a role in selected situations, depending on the pattern and extent of disease.
Depending on the tumour characteristics and stage, treatment may involve surgery, medical oncology, targeted treatments or other specialised therapies.
Confirm the tumour type and review pathology, imaging and relevant clinical findings.
Determine the extent of disease and evaluate whether the tumour is localised or has spread.
Select the appropriate combination of surgical and non-surgical treatment options.
Continued surveillance and further treatment are planned according to pathology and clinical findings.
The appropriate treatment depends on the type, location, grade and stage of the neuroendocrine tumour.
Surgery may be considered when the tumour can be safely and appropriately removed.
Certain hormone-producing or advanced NETs may be treated with medicines that target somatostatin receptors.
Depending on tumour characteristics, targeted medicines may form part of treatment for selected advanced neuroendocrine tumours.
Selected receptor-positive NETs may be considered for specialised radionuclide treatment as part of comprehensive oncology care.

Dr. Nitin Singhal is a surgical oncologist in Ahmedabad with experience in cancer surgery and complex gastrointestinal oncology.
For patients with neuroendocrine tumours, treatment planning involves understanding the tumour's location, pathology, grade, stage and relationship with surrounding structures before considering whether surgery may have a role.
Patients looking for a neuroendocrine tumour surgeon in Ahmedabad can undergo a detailed evaluation to understand the tumour's location, grade, stage and treatment options.
Neuroendocrine tumours may develop in the gastrointestinal tract, pancreas and other organs. Their behaviour can vary significantly, so treatment planning is based on individual pathology, imaging and clinical findings.
Surgery may be considered for selected gastrointestinal and pancreatic neuroendocrine tumours when the disease can be appropriately treated surgically. The surgical approach may be open, laparoscopic or robotic depending on the individual case.
Patients searching for NET treatment in Ahmedabad can discuss their pathology reports, imaging and previous treatment history with a surgical oncologist to understand whether surgery or another treatment approach may be appropriate.
Common questions about NET diagnosis, surgery and treatment planning.
A neuroendocrine tumour, or NET, is a tumour arising from neuroendocrine cells. NETs can occur in different organs and may behave differently depending on their grade, differentiation, location and stage.
NETs can occur in several parts of the body. Gastrointestinal NETs may involve the stomach, small intestine, appendix or colon, while pancreatic neuroendocrine tumours arise in the pancreas.
No. Treatment depends on the tumour's location, grade, stage, biological characteristics and overall clinical situation. Surgery may be appropriate for selected tumours, while other patients may require medical or other specialised treatments.
Robotic-assisted surgery may be considered for selected neuroendocrine tumour procedures when the tumour location, anatomy and planned operation make a minimally invasive approach appropriate.
Depending on the suspected tumour, evaluation may include biopsy and histopathology, immunohistochemistry, CT or MRI, endoscopic evaluation, biochemical tests and specialised functional imaging when appropriate.
tumour grade provides information about how quickly the tumour cells are dividing and is one of the factors used to understand the biological behaviour of a neuroendocrine tumour.
Some NETs can spread beyond their original site. The extent of disease is assessed using appropriate imaging, pathology and clinical evaluation and is important when deciding the treatment strategy.
Treatment planning considers the primary tumour location, grade, differentiation, stage, resectability, imaging findings, symptoms and overall health. Depending on the situation, treatment may involve surgery, medication or other specialised cancer therapies.
Get a personalised evaluation to understand your neuroendocrine tumour diagnosis, pathology, stage and whether surgery may have a role in your treatment.

Dr. Nitin Singhal has been recognised for his contribution to cancer care and surgical oncology, reflecting his commitment to advanced surgical techniques, clinical excellence and patient-centred care.
Surgical oncology training from Tata Memorial Hospital, Mumbai.
Expertise across complex and multidisciplinary cancer surgery.
Honoured for excellence in healthcare and surgical oncology.
Focus on evidence-based and personalised cancer treatment.
Recognition that reflects a continued commitment to excellence in cancer care.

