Comprehensive evaluation and treatment planning for vulval cancer, including vulval intraepithelial neoplasia and invasive disease, with treatment tailored according to tumour size, location, stage and lymph-node involvement.
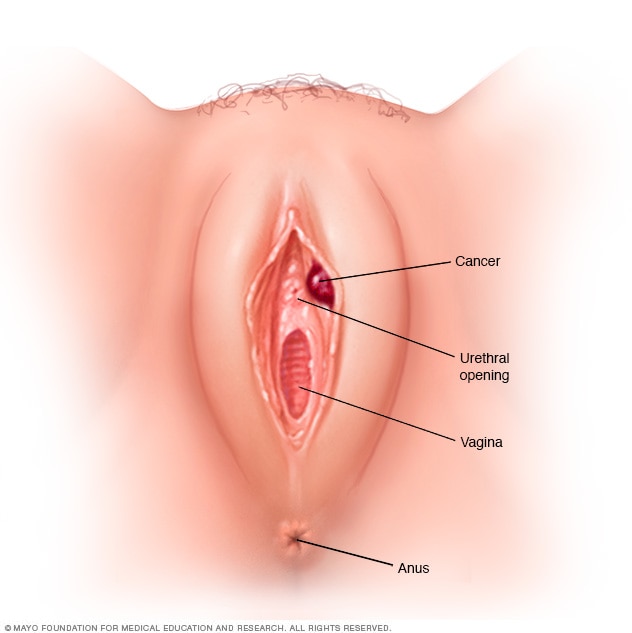
Vulval cancer develops in the external genitalia, collectively known as the vulva. The vulva includes the labia, clitoris, vaginal opening, urethral opening and surrounding external tissue.
Vulval cancer most commonly develops on the labia majora, although the labia minora, clitoris and Bartholin glands can also be affected.
Most invasive vulval cancers are squamous cell carcinomas. Other uncommon tumour types can occur and require individualised pathological assessment.
Vulval cancer develops in the external genitalia and is different from vaginal, cervical and uterine cancers.
The location of a vulval tumour can influence local surgery and the lymph nodes that need to be assessed.
The outer folds of the vulva. A large proportion of vulval squamous cell carcinomas arise in this region.
The inner folds surrounding the vaginal and urethral openings, which can also be affected by vulval cancer.
A sensitive structure at the front of the vulva. Tumours in this area require careful assessment because of its anatomy and function.
Glands located near the vaginal opening that can rarely be involved by vulval malignancy.
More than 90% of invasive vulval cancers are squamous cell carcinomas, arising from the squamous cells of the vulval skin.
A rare tumour that can develop from pigment-producing cells in the vulval area.
Rare glandular cancers can arise from structures such as the Bartholin glands.
Less common vulval malignancies require specialised pathological evaluation and treatment planning.
HPV infection is an important cause of many vulval cancers, particularly HPV-associated squamous cell cancers.
Persistent infection with certain high-risk human papillomavirus (HPV) types can cause abnormal changes in vulval cells.
NCI reports that HPV causes about half of all vulval cancers. HPV-related disease is more commonly associated with the basaloid and warty forms of vulval squamous cell carcinoma.
HPV vaccination can help prevent infection with HPV types that are associated with several cancers, including vulval cancer.
HPV is an important risk factor for vulval cancer, but not every vulval cancer is HPV-related.
VIN describes abnormal cells confined to the surface layer of the vulval skin and can precede invasive vulval cancer.
HPV-associated VIN is commonly seen in younger patients and is associated with high-risk HPV infection.
Differentiated VIN is generally not associated with HPV and is more often diagnosed in older women.
VIN may appear as an area of altered colour, thickening, a lump or another persistent skin change.
Selected VIN lesions may be treated with excision, laser treatment, skinning vulvectomy or topical imiquimod.
Vulval cancer may initially cause subtle skin changes. Persistent symptoms should be evaluated.
Vulval itching that does not resolve should be medically evaluated, particularly when associated with a visible skin change.
A new lump, wart-like growth, ulcer or thickened area can require examination and possibly biopsy.
A persistent change in the colour or appearance of vulval skin should be assessed.
Vulval bleeding that is not related to menstruation can be a symptom of vulval cancer.
Persistent pain or tenderness in the vulval area may require evaluation.
A sore or ulcer that does not heal normally should be assessed by a specialist.
Vulval cancer can develop through different pathways, including HPV-associated and non-HPV-associated disease.
Persistent infection with high-risk HPV types is an important risk factor for HPV-associated vulval cancer.
Certain forms of VIN can progress to invasive squamous cell carcinoma if they are not appropriately managed.
Increasing age is an important risk factor, particularly for non-HPV-associated vulval cancers.
Conditions or treatments that suppress the immune system can increase the risk of HPV-related vulval disease.
Certain long-standing inflammatory vulval skin disorders can be associated with increased risk.
Diagnosis usually begins with careful examination of the vulva and surrounding structures.
A biopsy of the abnormal area is essential to determine whether cancer or a precancerous lesion is present and to establish the tumour type.
Imaging such as MRI, CT or PET-CT may be used when appropriate to assess local extension, lymph nodes or distant disease.
A suspicious vulval lesion should be evaluated with appropriate tissue sampling before definitive treatment is planned.
The vulva is carefully inspected and palpated for abnormal skin changes, masses or ulcers.
Tissue from the suspicious area is examined by a pathologist to establish the diagnosis.
MRI, CT or PET-CT may help determine tumour extent and assess regional or distant disease.
The groin lymph nodes are particularly important because vulval cancer commonly spreads through the regional lymphatic system.
Early-stage disease may often be treated with local surgery, with the extent determined by tumour size, depth and location.
The tumour is removed together with a margin of surrounding normal tissue while preserving as much healthy vulval tissue as possible.
A deeper and wider local excision may be required when the tumour extends more deeply into the underlying tissue.
Modern surgery aims to remove the cancer while preserving as much normal vulval tissue and function as safely possible.
Removal of the cancer with an appropriate margin of surrounding tissue.
A larger and deeper local operation used for selected invasive tumours.
Removal of a larger portion of the vulva with regional lymph-node surgery when indicated.
Removal of the entire vulva may be considered for selected extensive tumours.
In selected early-stage vulval cancers, sentinel lymph node biopsy can help assess whether cancer has reached the groin lymph nodes.
Vulval cancer commonly spreads first to lymph nodes in the groin. Determining whether these nodes contain cancer is an important part of staging and treatment planning.
Sentinel lymph node assessment identifies the first lymph nodes that drain the tumour area. These nodes are removed and examined for cancer cells.
This approach is used only in appropriately selected patients and is not suitable for every vulval cancer.
Sentinel lymph node biopsy may reduce the need for more extensive groin lymph-node surgery in appropriately selected patients.
More extensive groin-node surgery may be required when the risk of lymph-node involvement is higher or when cancer is found in the sentinel nodes.
The lymph nodes in the groin are the primary regional lymph nodes for many vulval cancers.
Cancer found in sentinel nodes may lead to additional treatment depending on the extent of nodal involvement.
Selected patients may require removal of lymph nodes from the groin and upper thigh region.
Radiation may be recommended for selected patients with regional lymph-node involvement.
More extensive disease may involve the urethra, vagina, anus or regional lymph nodes and often requires multidisciplinary treatment.
Modified radical or radical vulvectomy with regional lymph-node surgery may be considered for selected locally advanced cancers.
Radiation can be used as definitive treatment or after surgery depending on tumour extent and risk factors.
Radiation combined with chemotherapy may be used in selected locally advanced cases.
Surgical oncology, radiation oncology and medical oncology may work together to determine the appropriate treatment sequence.
In selected patients, radiation with or without chemotherapy may be used before surgery to make local treatment possible or more effective.
When a tumour is difficult to remove safely because it involves nearby structures, radiation or chemoradiation may be considered before surgery.
The aim is to control the tumour locally and potentially allow subsequent surgery in carefully selected patients.
The sequence of treatment depends on tumour extent, patient factors and the multidisciplinary treatment plan.
Surgery may be performed before or after radiation-based treatment depending on the extent and characteristics of the cancer.
Treatment for stage IV or unresectable disease depends on the extent of spread, symptoms and previous treatment.
Radiation can be used to control local disease or relieve symptoms such as pain or bleeding.
Combined chemotherapy and radiation may be considered in selected patients with locally advanced disease.
Radical surgery or pelvic exenteration may be considered only for carefully selected patients with appropriate disease distribution.
Pelvic exenteration is an extensive operation that may be considered for selected patients with advanced or recurrent vulval cancer involving nearby pelvic organs.
Depending on the location and extent of disease, the operation may involve removal of structures such as the bladder, rectum, vagina and reproductive organs.
Because this is a major operation, careful multidisciplinary assessment is required before considering it.
Pelvic exenteration is not routine treatment and is considered only when the disease pattern and patient's condition make it a potential option.
Recurrent vulval cancer requires reassessment of the recurrence and all previous treatments.
A localized recurrence may be treated with wide local excision or more extensive surgery when appropriate.
Radiation may be considered depending on previous treatment and the location of the recurrent disease.
Chemotherapy and radiation may be considered for selected recurrent or locally advanced disease.
Radiation and other treatments may be used to control symptoms and support quality of life when cure is not possible.
Surgical planning aims to remove the cancer while preserving normal tissue and function whenever safely possible.
Wide local excision may allow preservation of more normal vulval tissue in selected early cancers.
Vulval surgery requires careful postoperative wound care and monitoring for healing complications.
Groin lymph-node surgery can affect lymphatic drainage and may increase the risk of leg or genital swelling.
Treatment planning should also consider sexual function, body image, comfort and emotional wellbeing.
Tumour location, depth, size and lymph-node status all contribute to the treatment decision.
Assess the location, appearance, size and relationship to nearby structures.
Biopsy determines whether the lesion is VIN or invasive cancer and establishes the tumour type.
Determine whether sentinel node biopsy or more extensive groin lymph-node assessment is appropriate.
Choose surgery, radiation, chemoradiation or a combined approach according to stage and individual factors.

Dr. Nitin Singhal is a surgical oncologist in Ahmedabad with experience in complex cancer surgery and multidisciplinary cancer care.
Vulval cancer treatment requires careful assessment of the primary tumour, surrounding structures and regional lymph nodes. Surgical options are planned according to the individual disease characteristics and overall treatment strategy.
Vulval cancer develops in the external genitalia and most commonly affects the labia. More than 90% of invasive vulval cancers are squamous cell carcinomas, while melanoma, adenocarcinoma and other rare tumours can also occur.
Persistent HPV infection is an important risk factor for many vulval cancers. Vulval intraepithelial neoplasia (VIN) represents abnormal cells confined to the surface of the vulval skin and can precede invasive cancer.
Persistent vulval itching, a lump or growth, a non-healing ulcer, abnormal bleeding, skin changes or vulval pain should be evaluated. Diagnosis generally involves clinical examination and biopsy, with MRI, CT or PET-CT used when appropriate for staging.
Surgery is the most common treatment for vulval cancer. Depending on the tumour, treatment may involve wide local excision, radical local excision, modified radical vulvectomy or radical vulvectomy. Sentinel lymph-node biopsy or inguinofemoral lymph-node surgery may be required depending on the stage and risk of nodal involvement.
Radiation therapy, chemotherapy and chemoradiation may be used for selected locally advanced, recurrent or extensive disease. Treatment is planned according to tumour stage, lymph-node status, previous treatment and the patient's overall health.
If you have been diagnosed with vulval cancer or have a persistent vulval lesion requiring evaluation, specialist assessment can help clarify the diagnosis, stage and available treatment options.
Common questions about vulval cancer symptoms, diagnosis, surgery and lymph-node treatment.
Get a personalised evaluation to understand your diagnosis, tumour stage, lymph-node status and available surgical and multidisciplinary treatment options.

Dr. Nitin Singhal has been recognised for his contribution to cancer care and surgical oncology, reflecting his commitment to advanced surgical techniques, clinical excellence and patient-centred care.
Surgical oncology training from Tata Memorial Hospital, Mumbai.
Expertise across complex and multidisciplinary cancer surgery.
Honoured for excellence in healthcare and surgical oncology.
Focus on evidence-based and personalised cancer treatment.
Recognition that reflects a continued commitment to excellence in cancer care.







